

- Home/
- Buy Clomid at Low Price in Australia Online
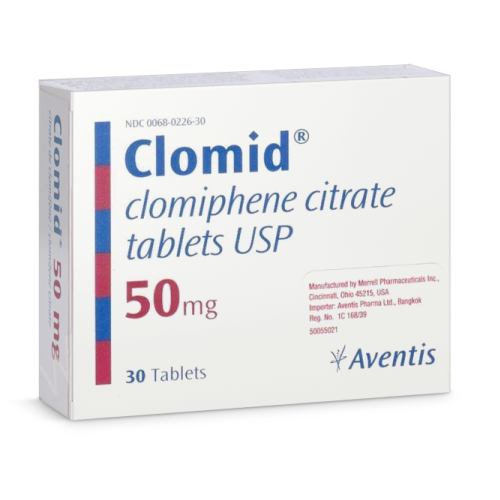
Clomid is a prescription-only fertility medication widely used in Australia to help women ovulate and improve their chances of pregnancy. Its active ingredient, clomiphene, stimulates the ovaries in a way that other medications do not. Before starting Clomid, it’s vital to know that while it can be highly effective for some, it’s not suitable for all causes of infertility, and its success depends on the right clinical scenario and careful monitoring by your doctor.
Why Clomid Is Still the First Word in Australian Fertility Clinics
Some words carry a quiet legacy in medicine. “Clomid” is one of them. If you’ve sat across from a fertility specialist anywhere from Sydney to Perth, you’ve probably heard it spoken with a kind of careful optimism. Not hype—just the sense that, for a certain kind of patient, this medication can transform the landscape of infertility.
For many Australian women facing irregular cycles or unexplained difficulties conceiving, Clomid is often the first intervention discussed after the basics have been checked. Its prominence isn’t just about history or habit. Clomid’s unique selling point is that it can coax the body into releasing eggs when it otherwise wouldn’t—without needing daily injections or hospital monitoring.
Most fertility clinics in Australia will suggest Clomid early if you are not ovulating regularly and other causes (such as blocked tubes or severe male factor) have been ruled out. This is what gives Clomid its enduring place—simple, accessible, and familiar to doctors and patients alike.
But Clomid’s reputation isn’t always matched by patient expectations. Some expect a miracle. Others fear side effects or are unsure if it’s still “modern medicine”. The reality? Both overestimation and underestimation miss the mark. Clomid is effective in the right clinical hands, and it’s the right choice only for some women—not for all causes of infertility. Knowing which group you belong to is the real art.
Will Clomid Actually Work for Me?
The most pressing question is rarely about Clomid’s chemical structure. It’s “How likely am I to get pregnant on this?”
- Clomid works best in women who aren’t ovulating regularly—especially those with polycystic ovary syndrome (PCOS)—but who still have enough functioning eggs and no major structural barriers to pregnancy.
- If your infertility has a different root—blocked tubes, low sperm count in your partner, or advanced age—Clomid’s odds drop off sharply.
- Most studies and real-world data from Australia show Clomid induces ovulation in about 70%-80% of suitable women. But the chance of a live birth per cycle is lower, typically 15-20% per month, depending on age, diagnosis, and timing.
That “per month” figure can mislead. Some women ovulate on Clomid but do not conceive—and often, other factors are at play. Others struggle to ovulate even with Clomid, and require an alternative approach. The true value of Clomid lies in careful patient selection, realistic expectations, and ongoing monitoring. For the right person, it opens a door. For others, it’s the wrong key.
“In practice, what matters most isn’t whether Clomid can work, but whether it should be tried first for you. That’s something your fertility specialist should walk through with you in detail—not everyone with infertility is a Clomid candidate, even if cycles are irregular.”
– Dr. Jessica Tran, MBBS FRANZCOG, Fertility Specialist, Sydney
So before you fill a script, make sure you know: Is my infertility due to ovulation problems? Are my tubes open? Is my partner’s fertility checked? If the answer is yes, Clomid may stand a real chance. If not, other options may suit you better.
Clomid, Letrozole, and Gonadotrophins: What’s Different in Real Life
| Attribute | Clomid (Clomiphene) | Letrozole | Gonadotrophins |
|---|---|---|---|
| Main Indication | Ovulation induction in women not ovulating regularly (esp. PCOS) | First-line for ovulation induction (esp. PCOS), increasing use | For women not responding to tablets, or for IVF protocols |
| Mechanism | Blocks oestrogen receptors, increases FSH/LH release | Aromatase inhibitor, lowers oestrogen, boosts FSH/LH | Injectable FSH/LH directly stimulates ovaries |
| Typical Regimen | Tablet, 5 days per month | Tablet, 5 days per month | Daily injections for 8-14 days per cycle |
| Effectiveness (Ovulation) | 70-80% | 70-80% (some data shows higher live birth rates) | 80-90% (higher risk of multiple pregnancies) |
| Common Side Effects | Hot flushes, mood swings, visual symptoms | Fatigue, headache, less effect on cervical mucus | Ovarian hyperstimulation, multiple pregnancies, injection site pain |
| Monitoring Needs | Low-moderate: ultrasound & bloods initially | Low-moderate: similar to Clomid | High: ultrasound/bloods every few days |
| Prescription Status (Australia) | Prescription-only, not PBS-listed | Prescription-only, not PBS-listed for infertility | Prescription-only, generally via fertility clinic |
| Typical Cost (Patient Pay) | Low ($20–$50 per cycle) | Low-moderate ($30–$60 per cycle) | High (hundreds to thousands per cycle) |
Here’s what the numbers miss: Clomid and letrozole are both oral tablets, but letrozole is sometimes preferred in PCOS due to slightly better pregnancy rates and fewer effects on cervical mucus or uterine lining. Gonadotrophins are more powerful, but carry higher risks, cost, and monitoring burdens—making them a last resort for most. In Australia, the decision is shaped as much by convenience, cost, and clinic protocols as by small differences in clinical trial outcomes. For many, Clomid remains the first step because it’s the simplest to start and the easiest to monitor, especially outside major urban centres.
How Clomid Gets Ovaries Moving – And When It Doesn’t
Clomid’s magic lies in how it “tricks” the brain. By blocking oestrogen’s effect on the hypothalamus, it makes the body sense low hormone levels. The brain responds by ramping up signals to the ovaries—resulting in one or more follicles maturing, and, with luck, ovulation. This is why Clomid only works if your ovaries and hormonal pathways are basically intact. It can’t create eggs or fix blocked tubes. It’s not a cure-all—it’s a nudge, and a precise one.
- Follicle
- A small sac in the ovary where an egg matures before ovulation.
- Ovulation Induction
- The process of stimulating the ovaries to release eggs, usually with medication.
Some women are “Clomid resistant”—meaning their bodies don’t respond even at higher doses. This is common in some women with PCOS, especially if weight or insulin resistance are factors. In these cases, alternatives like letrozole or injectable hormones may be considered. Clomid is also less likely to work well if ovarian reserve is low (as in older women) or when other infertility factors exist.
In practice, most clinics in Australia will start at 50mg daily for five days early in the cycle, increasing the dose if ovulation does not occur. Success is confirmed by blood tests and, sometimes, ultrasound tracking.
Taking Clomid in Australia: The Genuine Patient Experience
The first Clomid cycle rarely feels textbook-perfect. Most women walk into it with a head full of hope, worry, and half-remembered forum threads. Here’s how it actually unfolds, in the most common scenario:
- Consultation: Your fertility specialist reviews your history, checks your partner’s tests, and confirms Clomid is appropriate.
- Baseline Tests: Bloods and (sometimes) an ultrasound to check for cysts or pregnancy before starting.
- First Dose: You take one tablet daily for five days, usually starting between day 2 and day 5 of your period.
- Monitoring: Blood tests and/or ultrasound around day 10–14. Some clinics are rigorous, others more relaxed.
- Ovulation: With luck, you ovulate—signs include a rise in body temperature, a positive LH test, or symptoms like mild pain.
- Follow-Up: If no ovulation, dosage may increase next cycle. If you ovulate but don’t conceive after a few months, your doctor will review next steps.
Most women do not need daily hospital visits for Clomid cycles. Bloods and scans can often be done locally, with results sent to your specialist. This is a game-changer for regional and rural patients in Australia.
Clomid is almost always prescribed as a short course. In Australia, most doctors recommend no more than six cycles in total—both for effectiveness and to minimise rare risks like ovarian cysts or overstimulation. Remember, every skipped period or missed cycle matters for the timeline, so it’s crucial to follow your clinic’s guidance closely.
Which Side Effects Matter Most with Clomid – and When to Act
Most women tolerate Clomid without major issues. But side effects, when they occur, can be confusing or distressing. The most common complaints are hot flushes, mood swings, headaches, and visual disturbances. These rarely require stopping treatment, but they can be uncomfortable.
Visual symptoms—such as blurred vision, flashes, or spots—are a red flag. If these occur, stop the medication and call your doctor promptly. These symptoms, though rare, can indicate a reaction that requires discontinuation.
Less often, Clomid can cause ovarian cysts, pelvic pain, or—rarely—ovarian hyperstimulation syndrome (OHSS), a potentially serious complication. OHSS is uncommon with Clomid (much more frequent with injectable hormones), but symptoms like rapid weight gain, severe abdominal pain, shortness of breath, or vomiting require immediate medical attention.
Some women report emotional ups and downs—irritability, tearfulness, or anxiety. For most, these are mild and settle after the course finishes. If you find your mood or mental health is being significantly affected, let your doctor know; it may be possible to adjust your plan or provide extra support.
| Side Effect | How Common? | When to Call Your Doctor |
|---|---|---|
| Hot flushes | Very common (10-20%) | If severe or interfering with daily life |
| Headache | Common (up to 5%) | If persistent or associated with visual changes |
| Mood changes | Common (5-10%) | If severe, persistent, or impacting relationships |
| Visual symptoms (blurred vision, flashes) | Uncommon (<2%) | Immediately—stop medication and call doctor |
| Abdominal or pelvic pain | Common, usually mild | If severe, worsening, or associated with fever |
| Ovarian cysts | Uncommon | If pain is moderate to severe, or if persistent swelling |
| Ovarian hyperstimulation syndrome (OHSS) | Rare | Immediately if rapid weight gain, severe pain, vomiting, shortness of breath |
In practice, most side effects are transient and manageable. But it’s the rare and severe ones—especially vision changes and severe abdominal pain—that require immediate attention. If in doubt, call your clinic. They would rather you over-report than miss something important.
When Not to Take Clomid: Clinical Red Lines
- Never start Clomid if you are already pregnant. Confirm with a test before every cycle.
- Do not take Clomid if you have active liver disease or unexplained abnormal liver tests.
- It is contraindicated in women with ovarian cysts not due to PCOS, as it may worsen them.
- Known hormone-sensitive cancers (e.g., breast or uterine cancer) are clear exclusions.
- Unexplained abnormal vaginal bleeding must be fully investigated before considering Clomid.
Relative contraindications are more nuanced. Women with severe endometriosis, low ovarian reserve, or underlying cardiovascular risk require specialist input and closer monitoring. Some comorbidities (like poorly controlled thyroid disease) should be optimised before starting. Your specialist will also check your partner’s fertility—there’s little point stimulating ovulation if male factor infertility is present and untreated.
It’s never just about ticking boxes. The best clinics will say no to Clomid when it’s the wrong tool for the job—because time matters, and so does safety.
Getting Clomid in Australia: Prescription Rules, Costs, and Access
Clomid is prescription-only in Australia. It cannot be bought over the counter or legally sourced from online pharmacies without a valid Australian prescription. Unlike some other fertility medicines, Clomid is not subsidised by the Pharmaceutical Benefits Scheme (PBS) for infertility, meaning you will pay the full private price at the pharmacy—usually $20–$50 per cycle, depending on the brand and location.
Clomid is stocked by most retail pharmacies, but not all will keep it on the shelf. Your pharmacist may need to order it in, especially in rural areas. Always bring your prescription and allow a few days’ notice if starting a new cycle.
Australian fertility clinics typically provide a script after confirming your suitability for Clomid—often for several cycles at a time, with instructions for follow-up. Some doctors will require you to check in after each cycle before providing the next script, especially if monitoring is needed or side effects arise.
Private health insurance rarely covers the cost unless it is part of an inpatient process or a broader IVF package. Ask your clinic or insurer for specifics. Always keep receipts if you intend to claim as a medical expense at tax time. If you have concerns about affordability or access, speak to your GP or fertility nurse—there may be local support programs or hospital clinics available in some states.
Clomid in Australia: Frequently Asked Questions
- Is Clomid still the best first treatment for infertility in Australia?
- For many women with anovulatory infertility (especially PCOS), Clomid remains a first-line therapy, but letrozole is increasingly used and some specialists now prefer it for certain patients. The right choice depends on your diagnosis, age, and specific fertility goals. Discuss the options with your doctor.
- Can I get Clomid without a fertility specialist?
- Clomid requires a prescription in Australia, and while GPs can prescribe it, it is usually initiated by a fertility specialist after thorough assessment. Self-prescribing or obtaining it online without supervision is unsafe and may be illegal.
- How many cycles of Clomid should I try before moving on?
- Most Australian fertility clinics recommend up to six cycles. If there is no ovulation or pregnancy after 3-6 cycles, or if side effects or other factors intervene, your doctor will review your plan and may suggest alternatives.
- Is Clomid covered under the PBS or by private health insurance?
- Clomid is not listed on the PBS for infertility, so you pay full price at the pharmacy. Some private health insurance packages for IVF or inpatient treatment may cover it, but this is uncommon. Check with your provider.
- Are there long-term risks if I use Clomid for multiple cycles?
- Used as directed (no more than six cycles, with breaks as needed), long-term risks are considered low. There is no strong evidence linking Clomid to ovarian cancer when used appropriately, but your clinic will monitor for cysts and other rare complications.
- Can Clomid increase my chance of twins or higher-order multiples?
- Yes. Clomid increases the natural twin rate (about 6-8% chance vs 1-2% without treatment). Triplets are rare but possible. Proper monitoring reduces this risk. If you are worried about multiples, discuss this before starting.
- What if my cycles are regular, but I still can’t conceive—should I try Clomid?
- Clomid works by inducing ovulation. If you are already ovulating regularly, it is unlikely to improve your fertility and may even reduce pregnancy chances by affecting uterine lining or cervical mucus. Your doctor can run tests to confirm if Clomid is appropriate in your situation.
References
- Australian Government Department of Health, Therapeutic Goods Administration. https://www.tga.gov.au
- Royal Australian and New Zealand College of Obstetricians and Gynaecologists (RANZCOG). Female Infertility Clinical Practice Guidelines. 2022.
- Mayo Clinic. Clomiphene (Oral Route) Description and Brand Names. https://www.mayoclinic.org/drugs-supplements/clomiphene-oral-route/description/drg-20068741
- Fertility Society of Australia and New Zealand. Guidelines for Ovulation Induction. 2022.
- Product Information: Clomid (clomiphene citrate) tablets. Sanofi-Aventis Australia Pty Ltd.
- National Health Service (NHS). Infertility: Treatments. https://www.nhs.uk/conditions/infertility/treatment/
- World Health Organization (WHO). Infertility. https://www.who.int/news-room/fact-sheets/detail/infertility
- PubMed. Clinical studies on Clomiphene Citrate. https://pubmed.ncbi.nlm.nih.gov
